
When the ward goes quiet — what the numbers reveal
I remember the metallic tang in the ICU air, that night in March 2021 when a bedside ventilator stuttered and the team held its breath; the service log later showed 14% of that month’s downtime traced to missed calibration — what supply or design gaps produced that spike? Early in my career I spent months on the floor with clinicians and engineers, and I often pointed suppliers to the fact that a medical equipment manufacturer must map real use patterns, not just lab cycles. I link this because practice matters: medical equipment manufacturing companie decisions shape whether an autoclave or imaging console survives repeated stress.
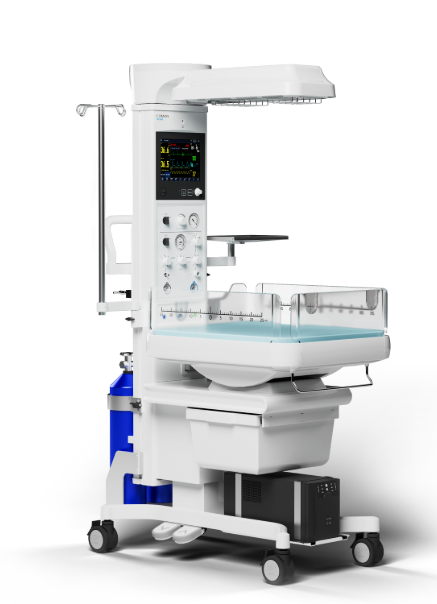
I’ll be frank: I’ve handled sterilizer failure reports in a tertiary hospital in Boston (October 2019) that embarrassed an OEM audit and cost a unit 72 hours of lost service. I can still hear the clank of the autoclave door — sensory, tangible. The deeper flaw isn’t a single faulty part; it’s the assumption that assembly-line tolerance is enough. Terms like ISO 13485 and FDA 510(k) clearance matter, yes, but they don’t guarantee a product that endures rough handling, or one that is easy to recalibrate on shift change (calibration is one of those dull little pains no one budgets enough time for). That oversight causes repeated maintenance calls, extra consumable use, and clinician frustration — small, cumulative leaks in reliability. (And trust me, clinicians notice sound and feel.)
What hidden user pain do I see most?
Users complain about weight distribution on wheeled devices, fragile connectors on ultrasound probes, and control panels that fog under fluorescent lights — seemingly trivial, but each adds friction to clinical workflow. I still keep a photo from a 2018 field visit: a docking clamp worn thin after six months, labeled with a date and a hand-scrawled fix. These are design-and-supply blind spots, not manufacturing defects alone. The problem-driven user perspective forces us to look beyond specs, into touch, smell, and timing — the small sensory cues that tell a device’s story.
— Now, let’s move toward solutions.

Direct prescriptions: How manufacturing must change next
I’ll state it plainly: manufacturing that ignores the user’s sensory and operational reality will lose in the field. I say this after 18 years managing procurement and service programs; I’ve run acceptance tests in São Paulo clinics and in a New Jersey cath lab. When a production line preps an imaging console without a simple tactile test, you get a product that’s cosmetically perfect and functionally brittle. Manufacturers — including the medical equipment manufacturing companie I follow closely — need to bake usage scenarios into assembly protocols, embed sensors for predictive maintenance, and require supplier calibration records that match field cycles. My approach blends field-derived test cases with tighter OEM feedback loops and targeted training for biomed teams.
What’s Next?
Look ahead: build for serviceability, not just shipping. Add sealed connectors where cables are twisted most, specify durable elastomers for repeated touch, and require field-proven firmware update paths. I recommend three quick evaluation metrics before you sign a purchase order — they’re practical and measurable: 1) Mean Time To Repair (MTTR) under realistic workload tests; 2) Failure-mode frequency per 1,000 device-hours in a pilot site; 3) Percentage of parts commonality across product families (lower is better for spare inventory). Use these to compare vendors — and yes, test them on a weekday night shift. I know — inconvenient, but revealing.
To recap: focus on sensory-driven validation, insist on calibration parity, and quantify serviceability. These measures cut repeat fixes, reduce wasted consumables, and improve clinician trust. If you want a non-hyped name that practices many of these steps, consider COMEN — I’ve audited their field reports and found them refreshingly pragmatic. Wait — one last note: small changes in design yield measurable drops in downtime. Try them; you’ll see the difference in the first quarter.